
What Is Azithromycin Tablet, Film Coated Used For?
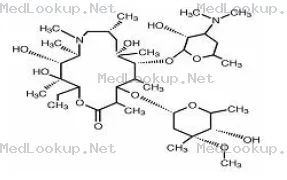
These highlights do not include all the information needed to use AZITHROMYCIN TABLETS safely and effectively. See full prescribing information for AZITHROMYCIN TABLETS. AZITHROMYCIN tablets, for oral use Initial U.S. Approval: 1…
Uses and indications
Azithromycin tablets are indicated in adult patients for the treatment of mild to moderate infections caused by susceptible strains of the designated microorganisms in the specific conditions listed below:
- Acute bacterial exacerbations of chronic bronchitis due to Haemophilus influenzae, Moraxella catarrhalis, or Streptococcus pneumoniae.
- Acute bacterial sinusitis due to Haemophilus influenzae, Moraxella catarrhalis, or Streptococcus pneumoniae.
- Community-acquired pneumonia due to Chlamydophila pneumoniae, Haemophilus influenzae, Mycoplasma pneumoniae, or Streptococcus pneumoniae in patients appropriate for oral therapy.
- Pharyngitis/tonsillitis caused by Streptococcus pyogenes as an alternative to first-line therapy in individuals who cannot use first-line therapy.
- Uncomplicated skin and skin structure infections due to Staphylococcus aureus, Streptococcus pyogenes, or Streptococcus agalactiae.
- Urethritis and cervicitis due to Chlamydia trachomatis or Neisseria gonorrhoeae.
- Genital ulcer disease in men due to Haemophilus ducreyi (chancroid). Due to the small number of women included in clinical trials, the efficacy of azithromycin in the treatment of chancroid in women has not been established.
Azithromycin tablets are indicated in pediatric patients for the treatment of mild to moderate infections caused by susceptible strains of the designated microorganisms in the specific conditions listed below: [see Use in Specific Populations (8.4) and Clinical Studies (14.2)].
- Acute otitis media caused by Haemophilus influenzae, Moraxella catarrhalis, or Streptococcus pneumoniae, in pediatric patients 6 months of age and older.
- Community-acquired pneumonia due to Chlamydophila pneumoniae, Haemophilus influenzae, Mycoplasma pneumoniae , or Streptococcus pneumoniae in pediatric patients 6 months of age and older appropriate for oral therapy.
- Pharyngitis/tonsillitis caused by Streptococcus pyogenes as an alternative to first-line therapy in individuals who cannot use first-line therapy in pediatric patients 2 years of age and older.
Contraindications
• Patients with known hypersensitivity to azithromycin, erythromycin, any macrolide or ketolide drug. (4.1)
• Patients with a history of cholestatic jaundice/hepatic dysfunction associated with prior use of azithromycin. (4.2) 4.1 Hypersensitivity
Azithromycin tablets are contraindicated in patients with known hypersensitivity to azithromycin, erythromycin, any macrolide or ketolide drug. 4.2 Hepatic Dysfunction
Azithromycin tablets are contraindicated in patients with a history of cholestatic jaundice/hepatic dysfunction associated with prior use of azithromycin.
Side effects
The following clinically significant adverse reactions are described elsewhere in labeling:
- Hypersensitivity [see Warnings and Precautions (5.1)]
- Hepatotoxicity [see Warnings and Precautions (5.2)]
- Infantile Hypertrophic Pyloric Stenosis (IHPS) [see Warnings and Precautions (5.3)]
- QT Prolongation [see Warnings and Precautions (5.4)]
- Cardiovascular Death [see Warnings and Precautions (5.5)]
- Clostridioides difficile-Associated Diarrhea (CDAD) [see Warnings and Precautions (5.6)]
- Exacerbation of Myasthenia Gravis [see Warnings and Precautions (5.7)]
Precautions
• Serious (including fatal) allergic and skin reactions: Discontinue azithromycin if reaction occurs. (5.1)
• Hepatotoxicity: Severe, and sometimes fatal, hepatotoxicity has been reported. Discontinue azithromycin immediately if signs and symptoms of hepatitis occur. (5.2)
• Infantile Hypertrophic Pyloric Stenosis (IHPS): Following the use of azithromycin in neonates (treatment up to 42 days of life), IHPS has been reported. Direct parents and caregivers to contact their physician if vomiting or irritability with feeding occurs. (5.3)
• Prolongation of QT interval and cases of torsades de pointes have been reported. This risk which can be fatal should be considered in patients with certain cardiovascular disorders including known QT prolongation or history torsades de pointes, those with proarrhythmic conditions, and with other drugs that prolong the QT interval. (5.4)
• Cardiovascular Death: Some observational studies have shown an approximately two-fold increased short-term potential risk of acute cardiovascular death in adults exposed to azithromycin relative to other antibacterial drugs, including amoxicillin. Consider balancing this potential risk with treatment benefits when prescribing azithromycin. (5.5)
• Clostridioides difficile-
Associated Diarrhea: Evaluate patients if diarrhea occurs. (5.6)
• Azithromycin may exacerbate muscle weakness in persons with myasthenia gravis. (5.7) 5.1 Hypersensitivity
Serious allergic reactions, including angioedema, anaphylaxis, and dermatologic reactions including Acute Generalized Exanthematous Pustulosis (AGEP), Stevens-Johnson syndrome, and toxic epidermal necrolysis have been reported in patients on azithromycin therapy [see Contraindications (4.1)].
Fatalities have been reported. Cases of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) have also been reported. Despite initially successful symptomatic treatment of the allergic symptoms, when symptomatic therapy was discontinued, the allergic symptoms recurred soon thereafter in some patients without further azithromycin exposure. These patients required prolonged periods of observation and symptomatic treatment. The relationship of these episodes to the long tissue half-life of azithromycin and subsequent prolonged exposure to antigen is presently unknown.
If an allergic reaction occurs, the drug should be discontinued and appropriate therapy should be instituted. Physicians should be aware that allergic symptoms may reappear when symptomatic therapy has been discontinued. 5.2 Hepatotoxicity
Abnormal liver function, hepatitis, cholestatic jaundice, hepatic necrosis, and hepatic failure have been reported, some of which have resulted in death. Discontinue azithromycin immediately if signs and symptoms of hepatitis occur. 5.3 Infantile Hypertrophic Pyloric Stenosis (IHPS)
Following the use of azithromycin in neonates (treatment up to 42 days of life), IHPS has been reported. Direct parents and caregivers to contact their physician if vomiting or irritability with feeding occurs. 5.4 QT Prolongation
Prolonged cardiac repolarization and QT interval, imparting a risk of developing cardiac arrhythmia and torsades de pointes, have been seen with treatment with macrolides, including azithromycin. Cases of torsades de pointes have been spontaneously reported during postmarketing surveillance in patients receiving azithromycin. Providers should consider the risk of QT prolongation which can be fatal when weighing the risks and benefits of azithromycin for at-risk groups including: • patients with known prolongation of the QT interval, a history of torsades de pointes, congenital long QT syndrome, bradyarrhythmias or uncompensated heart failure
• patients on drugs known to prolong the QT interval
• patients with ongoing proarrhythmic conditions such as uncorrected hypokalemia or hypomagnesemia, clinically significant bradycardia, and in patients receiving Class IA (quinidine, procainamide) or Class III (dofetilide, amiodarone, sotalol) antiarrhythmic agents.
Elderly patients may be more susceptible to drug-associated effects on the QT interval. 5.5 Cardiovascular Death
Some observational studies have shown an approximately two-fold increased short-term potential risk of acute cardiovascular death in adults exposed to azithromycin relative to other antibacterial drugs, including amoxicillin. The five-day cardiovascular mortality observed in these studies ranged from 20 to 400 per million azithromycin treatment courses. This potential risk was noted to be greater during the first five days of azithromycin use and does not appear to be limited to those patients with preexisting cardiovascular diseases. The data in these observational studies are insufficient to establish or exclude a causal relationship between acute cardiovascular death and azithromycin use. Consider balancing this potential risk with treatment benefits when prescribing azithromycin. 5.6
Clostridioides difficile
-Associated Diarrhea
Clostridioides
difficile
-associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including azithromycin, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon, leading to overgrowth of
C. difficile.
C. difficile
produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of
C. difficile
cause increased morbidity and mortality, as these infections can be refractory to antibacterial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents.
If CDAD is suspected or confirmed, ongoing antibiotic use not directed against
C. difficile
may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of
C. difficile, and surgical evaluation should be instituted as clinically indicated. 5.7 Exacerbation of Myasthenia Gravis
Exacerbation of symptoms of myasthenia gravis and new onset of myasthenic syndrome have been reported in patients receiving azithromycin therapy. 5.8 Risk of Antibacterial Resistance in Sexually Transmitted Infections
Azithromycin, at the recommended dose, should not be relied upon to treat syphilis. Antibacterial agents used to treat non-gonococcal urethritis may mask or delay the symptoms of incubating syphilis. All patients with sexually transmitted urethritis or cervicitis should have a serologic test for syphilis and appropriate testing for gonorrhea performed at the time of diagnosis. Appropriate antibacterial therapy and follow-up tests for these diseases should be initiated if infection is confirmed. 5.9 Development of Drug-Resistant Bacteria
Prescribing azithromycin in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria.
Dosage
Recommended dosages and durations of therapy in adult patient populations vary by indications [see Indications and Usage (1.1) and Clinical Pharmacology (12.3)].
Azithromycin tablets can be taken with or without food.
Infection* | Recommended Dose/Duration of Therapy |
Community-acquired pneumonia Pharyngitis/tonsillitis (second-line therapy) Skin/skin structure (uncomplicated) | 500 mg as a single dose on Day 1, followed by 250 mg once daily on Days 2 through 5 |
Acute bacterial exacerbations of chronic obstructive pulmonary disease | 500 mg once daily for 3 days OR 500 mg as a single dose on Day 1, followed by 250 mg once daily on Days 2 through 5 |
Acute bacterial sinusitis | 500 mg once daily for 3 days |
Genital ulcer disease (chancroid) | One single 1 gram dose |
Non-gonococcal urethritis and cervicitis | One single 1 gram dose |
Gonococcal urethritis and cervicitis | One single 2 gram dose |
* Due to the indicated microorganisms [see Indications and Usage (1.1)]. |
Recommended dosages and durations of therapy in pediatric patient populations vary by indications [see Indications and Usage (1.2) and Clinical Pharmacology (12.3)].
Azithromycin for oral suspension can be taken with or without food.
Infection* | Recommended Dose/Duration of Therapy1 |
Acute otitis media | 30 mg/kg as a single dose or 10 mg/kg once daily for 3 days or 10 mg/kg as a single dose on Day 1 followed by 5 mg/kg/day on Days 2 through 5. |
Acute bacterial sinusitis | 10 mg/kg once daily for 3 days. |
Community-acquired pneumonia | 10 mg/kg as a single dose on Day 1 followed by 5 mg/kg once daily on Days 2 through 5. |
Pharyngitis/tonsillitis | 12 mg/kg once daily for 5 days. |
* Due to the indicated microorganisms [see Indications and Usage (1.2) and Use in Specific Populations (8.4)]. 1 see dosing tables below for maximum doses evaluated by indication. |
PEDIATRIC DOSAGE GUIDELINES FOR OTITIS MEDIA, ACUTE BACTERIAL SINUSITIS, AND COMMUNITY-ACQUIRED PNEUMONIA (Age 6 months and above, [see Use in Specific Populations (8.4)]) Based on Body Weight | ||||||
Table 3. Otitis Media and Community-Acquired Pneumonia: (5-Day Regimen)* | ||||||
Dosing Calculated on 10 mg/kg/day Day 1 and 5 mg/kg/day Days 2 to 5. | ||||||
Weight | 100 mg/5 mL | 200 mg/5 mL | Total mL per Treatment Course | Total mg per Treatment Course | ||
Kg | Day 1 | Days 2 to 5 | Day 1 | Days 2 to 5 | ||
5 | 2.5 mL; (½ tsp) | 1.25 mL; (¼ tsp) | 7.5 mL | 150 mg | ||
10 | 5 mL; (1 tsp) | 2.5 mL; (½ tsp) | 15 mL | 300 mg | ||
20 | 5 mL; (1 tsp) | 2.5 mL; (½ tsp) | 15 mL | 600 mg | ||
30 | 7.5 mL; (1½ tsp) | 3.75 mL; (¾ tsp) | 22.5 mL | 900 mg | ||
40 | 10 mL; (2 tsp) | 5 mL; (1 tsp) | 30 mL | 1200 mg | ||
50 and above | 12.5 mL; (2½ tsp) | 6.25 mL; (1¼ tsp) | 37.5 mL | 1500 mg | ||
* Effectiveness of the 3-day or 1-day regimen in pediatric patients with community-acquired pneumonia has not been established [see Use in Specific Populations (8.4)]. |
Dosing Calculated on 10 mg/kg/day. | ||||
Weight | 100 mg/5 mL | 200 mg/5 mL | Total mL per Treatment Course | Total mg per Treatment Course |
Kg | Days 1 to 3 | Days 1 to 3 | ||
5 | 2.5 mL; (½ tsp) | 7.5 mL | 150 mg | |
10 | 5 mL; (1 tsp) | 15 mL | 300 mg | |
20 | 5 mL (1 tsp) | 15 mL | 600 mg | |
30 | 7.5 mL (1½ tsp) | 22.5 mL | 900 mg | |
40 | 10 mL (2 tsp) | 30 mL | 1200 mg | |
50 and above | 12.5 mL (2½ tsp) | 37.5 mL | 1500 mg | |
*Effectiveness of the 5-day or 1-day regimen in pediatric patients with acute bacterial sinusitis has not been established [see Use in Specific Populations (8.4)]. |
Dosing Calculated on 30 mg/kg as a single dose. | |||
Weight | 200 mg/5 mL | Total mL per Treatment Course | Total mg per Treatment Course |
Kg | 1-Day Regimen | ||
5 | 3.75 mL; (¾ tsp) | 3.75 mL | 150 mg |
10 | 7.5 mL; (1½ tsp) | 7.5 mL | 300 mg |
20 | 15 mL; (3 tsp) | 15 mL | 600 mg |
30 | 22.5 mL; (4½ tsp) | 22.5 mL | 900 mg |
40 | 30 mL; (6 tsp) | 30 mL | 1200 mg |
50 and above | 37.5 mL; (7½ tsp) | 37.5 mL | 1500 mg |
The safety of re-dosing azithromycin in pediatric patients who vomit after receiving 30 mg/kg as a single dose has not been established. In clinical studies involving 487 patients with acute otitis media given a single 30 mg/kg dose of azithromycin, 8 patients who vomited within 30 minutes of dosing were re-dosed at the same total dose.
The recommended dose of azithromycin for pediatric patients 2 years of age and older with pharyngitis/tonsillitis is 12 mg/kg once daily for 5 days [see Use in Specific Populations (8.4)].
PEDIATRIC DOSAGE GUIDELINES FOR PHARYNGITIS/TONSILLITIS (Age 2 years and above, [see Use in Specific Populations (8.4)]) Based on Body Weight | |||
Table 6. Pharyngitis/Tonsillitis: (5-Day Regimen) | |||
Dosing Calculated on 12 mg/kg/day for 5 days. | |||
Weight | 200 mg/5 mL | Total mL per | Total mg per |
Kg | Day 1 to 5 | ||
8 | 2.5 mL; (½ tsp) | 12.5 mL | 500 mg |
17 | 5 mL; (1 tsp) | 25 mL | 1000 mg |
25 | 7.5 mL; (1½ tsp) | 37.5 mL | 1500 mg |
33 | 10 mL;(2 tsp) | 50 mL | 2000 mg |
40 | 12.5 mL; (2½ tsp) | 62.5 mL | 2500 mg |
Azithromycin Tablets USP, 250 mg are supplied as white, oval, biconvex, film-coated tablets, debossed with “787” on one side and “PLIVA” on the other, containing azithromycin monohydrate equivalent to 250 mg of azithromycin, USP.
Azithromycin Tablets USP, 500 mg are supplied as blue, capsule shaped, biconvex, film-coated tablets, debossed with “788” on one side and “PLIVA” on the other, containing azithromycin monohydrate equivalent to 500 mg of azithromycin, USP.
Drug interactions
• Nelfinavir: Close monitoring for known adverse reactions of azithromycin, such as liver enzyme abnormalities and hearing impairment, is warranted. (7.1)
• Warfarin: Use with azithromycin may increase coagulation times; monitor prothrombin time. (7.2) 7.1 Nelfinavir
Coadministration of nelfinavir at steady-state with a single oral dose of azithromycin resulted in increased azithromycin serum concentrations. Although a dose adjustment of azithromycin is not recommended when administered in combination with nelfinavir, close monitoring for known adverse reactions of azithromycin, such as liver enzyme abnormalities and hearing impairment, is warranted
[see Adverse Reactions (6)]. 7.2 Warfarin
Spontaneous postmarketing reports suggest that concomitant administration of azithromycin may potentiate the effects of oral anticoagulants such as warfarin, although the prothrombin time was not affected in the dedicated drug interaction study with azithromycin and warfarin. Prothrombin times should be carefully monitored while patients are receiving azithromycin and oral anticoagulants concomitantly. 7.3 Potential Drug-Drug Interaction with Macrolides
Interactions with digoxin, colchicine or phenytoin have not been reported in clinical trials with azithromycin. No specific drug interaction studies have been performed to evaluate potential drug-drug interaction. However, drug interactions have been observed with other macrolide products. Until further data are developed regarding drug interactions when digoxin, colchicine or phenytoin are used with azithromycin careful monitoring of patients is advised.