
Aristada Injection, Suspension, Extended Release
These highlights do not include all the information needed to use ARISTADA® safely and effectively. See full prescribing information for ARISTADA®. ARISTADA® (aripiprazole lauroxil) extended-release injectable suspension, for int…
Uses and indications
ARISTADA is indicated for the treatment of schizophrenia in adults [see Clinical Studies (14)].
Contraindications
ARISTADA is contraindicated in patients with a known hypersensitivity reaction to aripiprazole. Hypersensitivity reactions have ranged from pruritus/urticaria to anaphylaxis [see Adverse Reactions (6)].
Side effects
In placebo-controlled trials with risperidone, aripiprazole, and olanzapine in elderly patients with dementia, there was a higher incidence of cerebrovascular adverse reactions (cerebrovascular accidents and transient ischemic attacks) including fatalities compared to placebo-treated patients. ARISTADA is not approved for the treatment of patients with dementia-related psychosis [see Boxed Warning, Warnings and Precautions ( 5.1 )].
The following are discussed in more details in other sections of the labeling:
- Increased Mortality in Elderly Patients with Dementia-related Psychosis [see Boxed Warning, Warnings and Precautions ( 5.1 )]
- Cerebrovascular Adverse Reactions, Including Stroke [see Boxed Warning, Warnings and Precautions ( 5.2 )]
- Neuroleptic Malignant Syndrome [see Warnings and Precautions ( 5.4 )]
- Tardive Dyskinesia [see Warnings and Precautions ( 5.5 )]
- Metabolic Changes [see Warnings and Precautions ( 5.6 )]
- Pathological Gambling and Other Compulsive Behaviors [see Warnings and Precautions ( 5.7 )]
- Orthostatic Hypotension [see Warnings and Precautions ( 5.8 )]
- Falls [see Warnings and Precautions ( 5.9 )]
- Leukopenia, Neutropenia, and Agranulocytosis [see Warnings and Precautions ( 5.10 )]
- Seizures [see Warnings and Precautions ( 5.11 )]
- Potential for Cognitive and Motor Impairment [see Warnings and Precautions ( 5.12 )]
- Body Temperature Regulation [see Warnings and Precautions ( 5.13 )]
- Dysphagia [see Warnings and Precautions ( 5.14 )]
Precautions
• Cerebrovascular Adverse Reactions in Elderly Patients with Dementia-Related Psychosis: Increased incidence of cerebrovascular adverse reactions (e.g., stroke, transient ischemia attack, including fatalities) (5.2).
• Potential for Dosing and Medication Errors
: Substitution and dispensing errors between ARISTADA and ARISTADA INITIO could occur. Do not substitute ARISTADA INITIO for ARISTADA (5.3).
• Neuroleptic Malignant Syndrome
: Manage with immediate discontinuation and close monitoring (5.4).
• Tardive Dyskinesia
: Discontinue if clinically appropriate (5.5).
• Metabolic Changes
: Monitor for hyperglycemia, dyslipidemia, and weight gain (5.6).
• Pathological Gambling and Other Compulsive Behaviors
: Consider dose reduction or discontinuation (5.7).
• Orthostatic Hypotension
: Monitor heart rate and blood pressure and warn patients with known cardiovascular or cerebrovascular disease, and risk of dehydration or syncope (5.8).
• Leukopenia, Neutropenia, and Agranulocytosis
: Perform complete blood counts in patients with a history of a clinically significant low white blood cell (WBC) count. Consider discontinuation if clinically significant decline in WBC in the absence of other causative factors (5.10).
• Seizures
: Use cautiously in patients with a history of seizures or with conditions that lower the seizure threshold (5.11).
• Potential for Cognitive and Motor Impairment
: Use caution when operating machinery (5.12). 5.1 Increased Mortality in Elderly Patients with Dementia-related Psychosis
Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of 17 placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear. ARISTADA is not approved for the treatment of patients with dementia-related psychosis
[see Boxed Warning, Warnings and Precautions
(5.2)]. 5.2 Cerebrovascular Adverse Reactions, Including Stroke
In placebo-controlled trials with risperidone, aripiprazole, and olanzapine in elderly patients with dementia, there was a higher incidence of cerebrovascular adverse reactions (cerebrovascular accidents and transient ischemic attacks) including fatalities compared to placebo-treated patients. ARISTADA is not approved for the treatment of patients with dementia-related psychosis
[see Boxed Warning, Warnings and Precautions
(5.1)]. 5.3 Potential for Dosing and Medication Errors
Medication errors, including substitution and dispensing errors, between ARISTADA and ARISTADA INITIO could occur. ARISTADA INITIO is for single administration in contrast to ARISTADA which is administered monthly, every 6 weeks, or every 8 weeks
[see Dosage and Administration (2.1)]. Do not substitute ARISTADA INITIO for ARISTADA because of differing pharmacokinetic profiles
[see Clinical Pharmacology
(12.3)]. 5.4 Neuroleptic Malignant Syndrome
A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) may occur in association with antipsychotic drugs, including ARISTADA. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia). Additional signs may include elevated creatine phosphokinase, myoglobinuria (rhabdomyolysis), and acute renal failure.
The diagnostic evaluation of patients with this syndrome is complicated. In arriving at a diagnosis, it is important to identify cases in which the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.) and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever, and primary central nervous system pathology.
The management of NMS should include: (1) immediate discontinuation of antipsychotic drugs and other drugs not essential to concurrent therapy; (2) intensive symptomatic treatment and medical monitoring; and (3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacological treatment regimens for uncomplicated NMS.
If a patient appears to require antipsychotic drug treatment after recovery from NMS, reintroduction of drug therapy should be closely monitored, since recurrences of NMS have been reported. 5.5 Tardive Dyskinesia
A syndrome of potentially irreversible, involuntary, dyskinetic movements may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to predict which patients will develop the syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown.
The risk of developing tardive dyskinesia and the likelihood that it will become irreversible appear to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase, but the syndrome can develop after relatively brief treatment periods at low doses, although this is uncommon.
Tardive dyskinesia may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment itself may suppress (or partially suppress) the signs and symptoms of the syndrome and may thus mask the underlying process. The effect of symptomatic suppression on the long-term course of the syndrome is unknown.
Given these considerations, ARISTADA should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that is known to respond to antipsychotic drugs. In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically.
If signs and symptoms of tardive dyskinesia appear in a patient treated with ARISTADA drug discontinuation should be considered. However, some patients may require treatment with ARISTADA despite the presence of the syndrome. 5.6 Metabolic Changes
Atypical antipsychotic drugs have been associated with metabolic changes that include hyperglycemia/diabetes mellitus, dyslipidemia, and weight gain. While all drugs in the class have been shown to produce some metabolic changes, each drug has its own specific risk profile. Hyperglycemia/ Diabetes Mellitus
Hyperglycemia, in some cases extreme and associated with ketoacidosis or hyperosmolar coma or death, has been reported in patients treated with atypical antipsychotics. There have been reports of hyperglycemia in patients treated with oral aripiprazole. Assessment of the relationship between atypical antipsychotic use and glucose abnormalities is complicated by the possibility of an increased background risk of diabetes mellitus in patients with schizophrenia and the increasing incidence of diabetes mellitus in the general population. Given these confounders, the relationship between atypical antipsychotic use and hyperglycemia-related adverse events is not completely understood. However, epidemiological studies suggest an increased risk of hyperglycemia-related adverse reactions in patients treated with the atypical antipsychotics.
Patients with an established diagnosis of diabetes mellitus who are started on atypical antipsychotics should be monitored regularly for worsening of glucose control. Patients with risk factors for diabetes mellitus (e.g., obesity, family history of diabetes) who are starting treatment with atypical antipsychotics should undergo fasting blood glucose testing at the beginning of treatment and periodically during treatment. Any patient treated with atypical antipsychotics should be monitored for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients who develop symptoms of hyperglycemia during treatment with atypical antipsychotics should undergo fasting blood glucose testing. In some cases, hyperglycemia has resolved when the atypical antipsychotic was discontinued; however, some patients require continuation of anti-diabetic treatment despite discontinuation of the suspect drug.
In the long-term, open-label schizophrenia study with ARISTADA, 14% of patients with normal hemoglobin A1c (<5.7%) at baseline developed elevated levels (≥5.7%) post-baseline. Dyslipidemia
Undesirable alterations in lipids have been observed in patients treated with atypical antipsychotics.
In the long-term, open-label schizophrenia study with ARISTADA, shifts in baseline fasting total cholesterol from normal (<200 mg/dL) to high (≥240 mg/dL) were reported in 1% of patients; shifts in baseline fasting LDL cholesterol from normal (<100 mg/dL) to high (≥160 mg/dL) were reported in 1% of patients; and shifts in baseline fasting triglycerides from normal (<150 mg/dL) to high (≥200 mg/dL) were reported in 8% of patients. In the same study, shifts in baseline fasting total cholesterol from borderline (≥ 200 mg/dL and <240 mg/dL) to high (≥240 mg/dL) were reported in 15% of patients; shifts in baseline fasting LDL cholesterol from borderline (≥100 mg/dL and <160 mg/dL) to high (≥160 mg/dL) were reported in 8% of patients; and shifts in baseline fasting triglycerides from borderline (≥150 mg/dL and <200 mg/dL) to high (≥200 mg/dL) were reported in 35% of patients. In addition, the proportion of patients with shifts in fasting HDL cholesterol from normal (≥40 mg/dL) to low (<40 mg/dL) was reported in 15% of patients. Weight Gain
Weight gain has been observed with atypical antipsychotic use. Clinical monitoring of weight is recommended.
The proportion of adult patients with weight gain ≥7% of body weight is presented in Table 7.
Table 7: Proportion of Adult Patients with Shifts in Weight in the 12-Week, Placebo-Controlled, Fixed-Dose Schizophrenia Trial
Placebo N = 207 (%)
ARISTADA
441 mg N = 207 (%)
882 mg N = 208 (%)
Weight Gain
≥7% increase from baseline
6
10
9 5.7 Pathological Gambling and Other Compulsive Behaviors
Post-marketing case reports suggest that patients can experience intense urges, particularly for gambling, and the inability to control these urges while taking aripiprazole. Other compulsive urges, reported less frequently include: sexual urges, shopping, eating or binge eating, and other impulsive or compulsive behaviors. Because patients may not recognize these behaviors as abnormal, it is important for prescribers to ask patients or their caregivers specifically about the development of new or intense gambling urges, compulsive sexual urges, compulsive shopping, binge or compulsive eating, or other urges while being treated with aripiprazole. It should be noted that impulse-control symptoms can be associated with the underlying disorder. In some cases, although not all, urges were reported to have stopped when the dose was reduced or the medication was discontinued. Compulsive behaviors may result in harm for the patient and others if not recognized. Consider dose reduction or stopping the medication if a patient develops such urges. 5.8 Orthostatic Hypotension
Aripiprazole may cause orthostatic hypotension, perhaps due to its α1-adrenergic receptor antagonism. Associated adverse reactions related to orthostatic hypotension can include dizziness, lightheadedness and tachycardia. Generally, these risks are greatest at the beginning of treatment and during dose escalation. Patients at increased risk of these adverse reactions or at increased risk of developing complications from hypotension include those with dehydration, hypovolemia, treatment with antihypertensive medication, history of cardiovascular disease (e.g., heart failure, myocardial infarction, ischemia, or conduction abnormalities), history of cerebrovascular disease, as well as patients who are antipsychotic-naïve. In such patients, consider using a lower starting dose, and monitor orthostatic vital signs.
Orthostatic hypotension was reported for one patient in the ARISTADA 882 mg group (0.5%) and no patients in the ARISTADA 441 mg and placebo groups in the 12-week schizophrenia efficacy study [see Clinical Studies (14)]. In the long-term open-label schizophrenia study, orthostatic hypotension was reported for 1 (0.2%) patient treated with ARISTADA. Orthostatic hypotension was defined as a decrease in systolic blood pressure ≥20 mmHg accompanied by an increase in heart rate ≥25 bpm when comparing standing to supine values. 5.9 Falls
Antipsychotics including ARISTADA may cause somnolence, postural hypotension, or motor and sensory instability, which may lead to falls and, consequently, fractures or other injuries. For patients with diseases, conditions, or medications that could exacerbate these effects, complete fall risk assessments when initiating antipsychotic treatment and recurrently for those patients on long-term antipsychotic therapy. 5.10 Leukopenia, Neutropenia, and Agranulocytosis
In clinical trials and/or postmarketing experience, events of leukopenia and neutropenia have been reported temporally related to antipsychotic agents. Agranulocytosis has also been reported.
Possible risk factors for leukopenia/neutropenia include pre-existing low white blood cell count (WBC)/absolute neutrophil count (ANC) and history of drug-induced leukopenia/neutropenia. In patients with a history of a clinically significant low WBC/ANC or drug-induced leukopenia/neutropenia, perform a complete blood count (CBC) frequently during the first few months of therapy. In such patients, consider discontinuation of ARISTADA at the first sign of a clinical significant decline in WBC in the absence of other causative factors.
Monitor patients with clinically significant neutropenia for fever or other symptoms or signs of infection and treat promptly if such symptoms or signs occur. Discontinue ARISTADA in patients with severe neutropenia (absolute neutrophil count <1000/mm3) and follow their WBC until recovery. 5.11 Seizures
As with other antipsychotic drugs, use ARISTADA cautiously in patients with a history of seizures or with conditions that lower the seizure threshold. Conditions that lower the seizure threshold may be more prevalent in a population of 65 years or older. 5.12 Potential for Cognitive and Motor Impairment
ARISTADA, like other antipsychotics, has the potential to impair judgment, thinking or motor skills. Patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that therapy with ARISTADA does not affect them adversely. 5.13 Body Temperature Regulation
Disruption of the body's ability to reduce core body temperature has been attributed to antipsychotic agents. Appropriate care is advised when prescribing ARISTADA for patients who will be experiencing conditions which may contribute to an elevation in core body temperature, (e.g., exercising strenuously, exposure to extreme heat, receiving concomitant medication with anticholinergic activity, or being subject to dehydration). 5.14 Dysphagia
Esophageal dysmotility and aspiration have been associated with antipsychotic drug use. ARISTADA and other antipsychotic drugs should be used cautiously in patients at risk for aspiration pneumonia.
Dosage
ARISTADA is only to be administered as an intramuscular injection by a healthcare professional. For patients who have never taken aripiprazole, establish tolerability with oral aripiprazole prior to initiating treatment with ARISTADA. Due to the half-life of oral aripiprazole, it may take up to 2 weeks to fully assess tolerability. Refer to the prescribing information of oral aripiprazole for the recommended dosage and administration of the oral formulation.
There are two ways to initiate treatment with ARISTADA:
- Option #1: Administer one intramuscular injection of ARISTADA INITIO 675 mg (in either the deltoid or gluteal muscle) and one dose of oral aripiprazole 30 mg in conjunction with the first ARISTADA injection.
- The first ARISTADA injection may be administered on the same day as ARISTADA INITIO or up to 10 days thereafter. See the ARISTADA INITIO prescribing information for additional information regarding administration of ARISTADA INITIO.
- Avoid injecting both ARISTADA INITIO and ARISTADA concomitantly into the same deltoid or gluteal muscle.
- Option #2: Administer 21 consecutive days of oral aripiprazole in conjunction with the first ARISTADA injection.
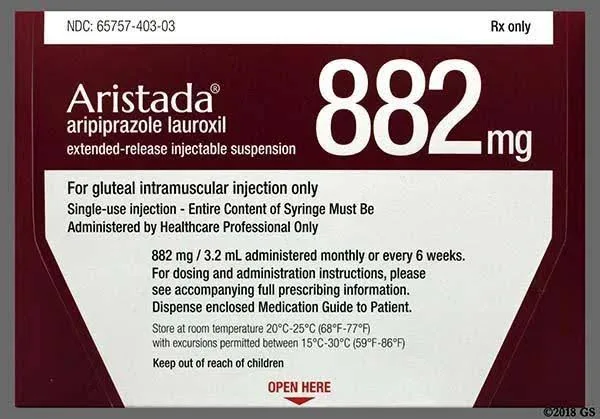
Depending on individual patient's needs, treatment with ARISTADA can be initiated at a dose of 441 mg, 662 mg or 882 mg administered monthly, 882 mg administered every 6 weeks or 1064 mg administered every 2 months. The 441 mg, 662 mg, 882 mg and 1064 mg doses correspond to 300 mg, 450 mg, 600 mg and 724 mg of aripiprazole, respectively [see Clinical Pharmacology (12.3)].
| Dose | Dosing Frequency | Site of Intramuscular Injection |
|---|---|---|
| 441 mg | Monthly | Deltoid or Gluteal |
| 662 mg | Monthly | Gluteal |
| 882 mg | Monthly or every 6 weeks | Gluteal |
| 1064 mg | Every 2 months | Gluteal |
Use the following ARISTADA doses for patients who are stabilized on oral aripiprazole, as shown in Table 2.
| Oral Aripiprazole Dose | Intramuscular ARISTADA Dose |
|---|---|
| 10 mg per day | 441 mg every month |
| 15 mg per day | 662 mg every month 882 mg every 6 weeks 1064 mg every 2 months |
| 20 mg or higher per day | 882 mg every month |
In conjunction with the first ARISTADA injection, administer a single injection of ARISTADA INITIO and one dose of oral aripiprazole 30 mg, or continue treatment with oral aripiprazole for 21 consecutive days [see Recommended Dosage ( 2.1)].
Adjust the ARISTADA dose as needed. When making dose and dosing interval adjustments, consider the pharmacokinetics and prolonged-release characteristics of ARISTADA [see Clinical Pharmacology ( 12.3 )].
ARISTADA is a white to off-white aqueous extended-release injectable suspension provided in a single-dose pre-filled syringe.
ARISTADA is available as described in Table 6.
| Dose Strength | Volume | Inject Intramuscularly | Color Label |
|---|---|---|---|
| 441 mg | 1.6 mL | Deltoid or Gluteal Muscle | Light Blue |
| 662 mg | 2.4 mL | Gluteal Muscle Only | Green |
| 882 mg | 3.2 mL | Gluteal Muscle Only | Burgundy |
| 1064 mg | 3.9 mL | Gluteal Muscle Only | Dark Blue |
Drug interactions
| Strong CYP3A4 Inhibitors and CYP2D6 Inhibitors | |
| Clinical Impact: | The concomitant use of oral aripiprazole with strong CYP3A4 or CYP2D6 inhibitors increased the exposure of aripiprazole compared to the use of oral aripiprazole alone [see Clinical Pharmacology ( 12.3 )]. |
| Intervention: | With concomitant use of ARISTADA with a strong CYP3A4 inhibitor or CYP2D6 inhibitor for more than 2 weeks, reduce the ARISTADA dose [see Dosage and Administration ( 2.4 )]. |
| Examples: | itraconazole, clarithromycin, quinidine, fluoxetine, paroxetine |
| Strong CYP3A4 Inducers | |
| Clinical Impact: | The concomitant use of oral aripiprazole and carbamazepine decreased the exposure of aripiprazole compared to the use of oral aripiprazole alone [see Clinical Pharmacology ( 12.3 )]. |
| Intervention: | With concomitant use of ARISTADA with a strong CYP3A4 inducer for more than 2 weeks consider increasing the ARISTADA dose [see Dosage and Administration ( 2.4 )]. |
| Examples: | carbamazepine, rifampin |
| Antihypertensive Drugs | |
| Clinical Impact: | Due to its alpha adrenergic antagonism, aripiprazole has the potential to enhance the effect of certain antihypertensive agents. |
| Intervention: | Monitor blood pressure and adjust dose accordingly [see Warnings and Precautions ( 5.8 )]. |
| Examples: | carvedilol, lisinopril, prazosin |
| Benzodiazepines | |
| Clinical Impact: | The intensity of sedation was greater with the combination of oral aripiprazole and lorazepam as compared to that observed with aripiprazole alone. The orthostatic hypotension observed was greater with the combination as compared to that observed with lorazepam alone [see Warnings and Precautions ( 5.8 )]. |
| Intervention: | Monitor sedation and blood pressure. Adjust dose accordingly. |
| Example: | lorazepam |
Based on pharmacokinetic studies with oral aripiprazole, no dosage adjustment of ARISTADA is required when administered concomitantly with famotidine, valproate, or lithium [see Clinical Pharmacology ( 12.3 )].
In addition, no dosage adjustment is necessary for substrates of CYP2D6 (e.g., dextromethorphan, fluoxetine, paroxetine, or venlafaxine), CYP2C9 (e.g., warfarin), CYP2C19 (e.g., omeprazole, warfarin, escitalopram), or CYP3A4 (e.g., dextromethorphan) when co-administered with ARISTADA. Additionally, no dosage adjustment is necessary for valproate, lithium, lamotrigine, or sertraline when co-administered with ARISTADA [see Clinical Pharmacology ( 12.3 )].